Specialist hernia surgeon in Edinburgh

Expert assessment, clear advice and treatment tailored to you

Mr Ben Stutchfield

Consultant General and Transplant Surgeon, Royal Infirmary Edinburgh. Private consultations at Spire Murrayfield and Spire Shawfair Park.​

Consultant Surgeon Ben Stutchfield

Specialist hernia surgeon in Edinburgh

Expert assessment, clear advice and treatment tailored to you

Mr Ben Stutchfield

Consultant General and Transplant Surgeon, Royal Infirmary Edinburgh. Private consultations at Spire Murrayfield and Spire Shawfair Park.​

Consultant Surgeon Ben Stutchfield

Specialist hernia surgeon in Edinburgh

Expert assessment, clear advice and treatment tailored to you​

Consultant Surgeon Ben Stutchfield

Mr Ben Stutchfield

Consultant General and Transplant Surgeon, Royal Infirmary Edinburgh. Private consultations at Spire Murrayfield and Spire Shawfair Park.​

Could a hernia be causing my symptoms?

An abdominal bulge, discomfort or heaviness may suggest a hernia

Do I need hernia surgery?

Some patients can be managed conservatively, while others benefit from hernia repair depending on their symptoms, examination findings and overall health

Evidence based care, tailored to you

ABOUT MR STUTCHFIELD

Mr Ben Stutchfield is a consultant transplant and general surgeon at the Royal Infirmary in Edinburgh, where he performs liver transplantation, works within the specialist hernia team and performs gallbladder surgery. He brings this experience and expertise to his private practice, offering evidence-based care tailored to each person.

Appointed as a consultant in 2019, Mr Stutchfield trained extensively in transplantation, biliary, and hernia surgery and holds a PhD in regenerative medicine from the University of Edinburgh. 

He specialises in hernia repair, abdominal wall reconstruction, and gallbladder (gallstone) surgery, offering both minimally invasive laparoscopic (keyhole) and open procedures at Spire Murrayfield and Shawfair Park Hospitals

His current research interests include abdominal wall reconstruction techniques as well as understanding how algorithms and clinicians can best interact to improve patient outcomes. He has published research in the Lancet as well as other specialist journals. He serves as a reviewer for several specialist surgical journals. 

His focus is on delivering safe, effective and personalised treatment using the latest surgical techniques to achieve the best possible outcomes for patients. 

How does a hernia develop?

A hernia happens when tissue from inside the abdomen pushes through a weak spot in the muscle wall. Most start small and grow slowly over time. Select each stage to see what happens.
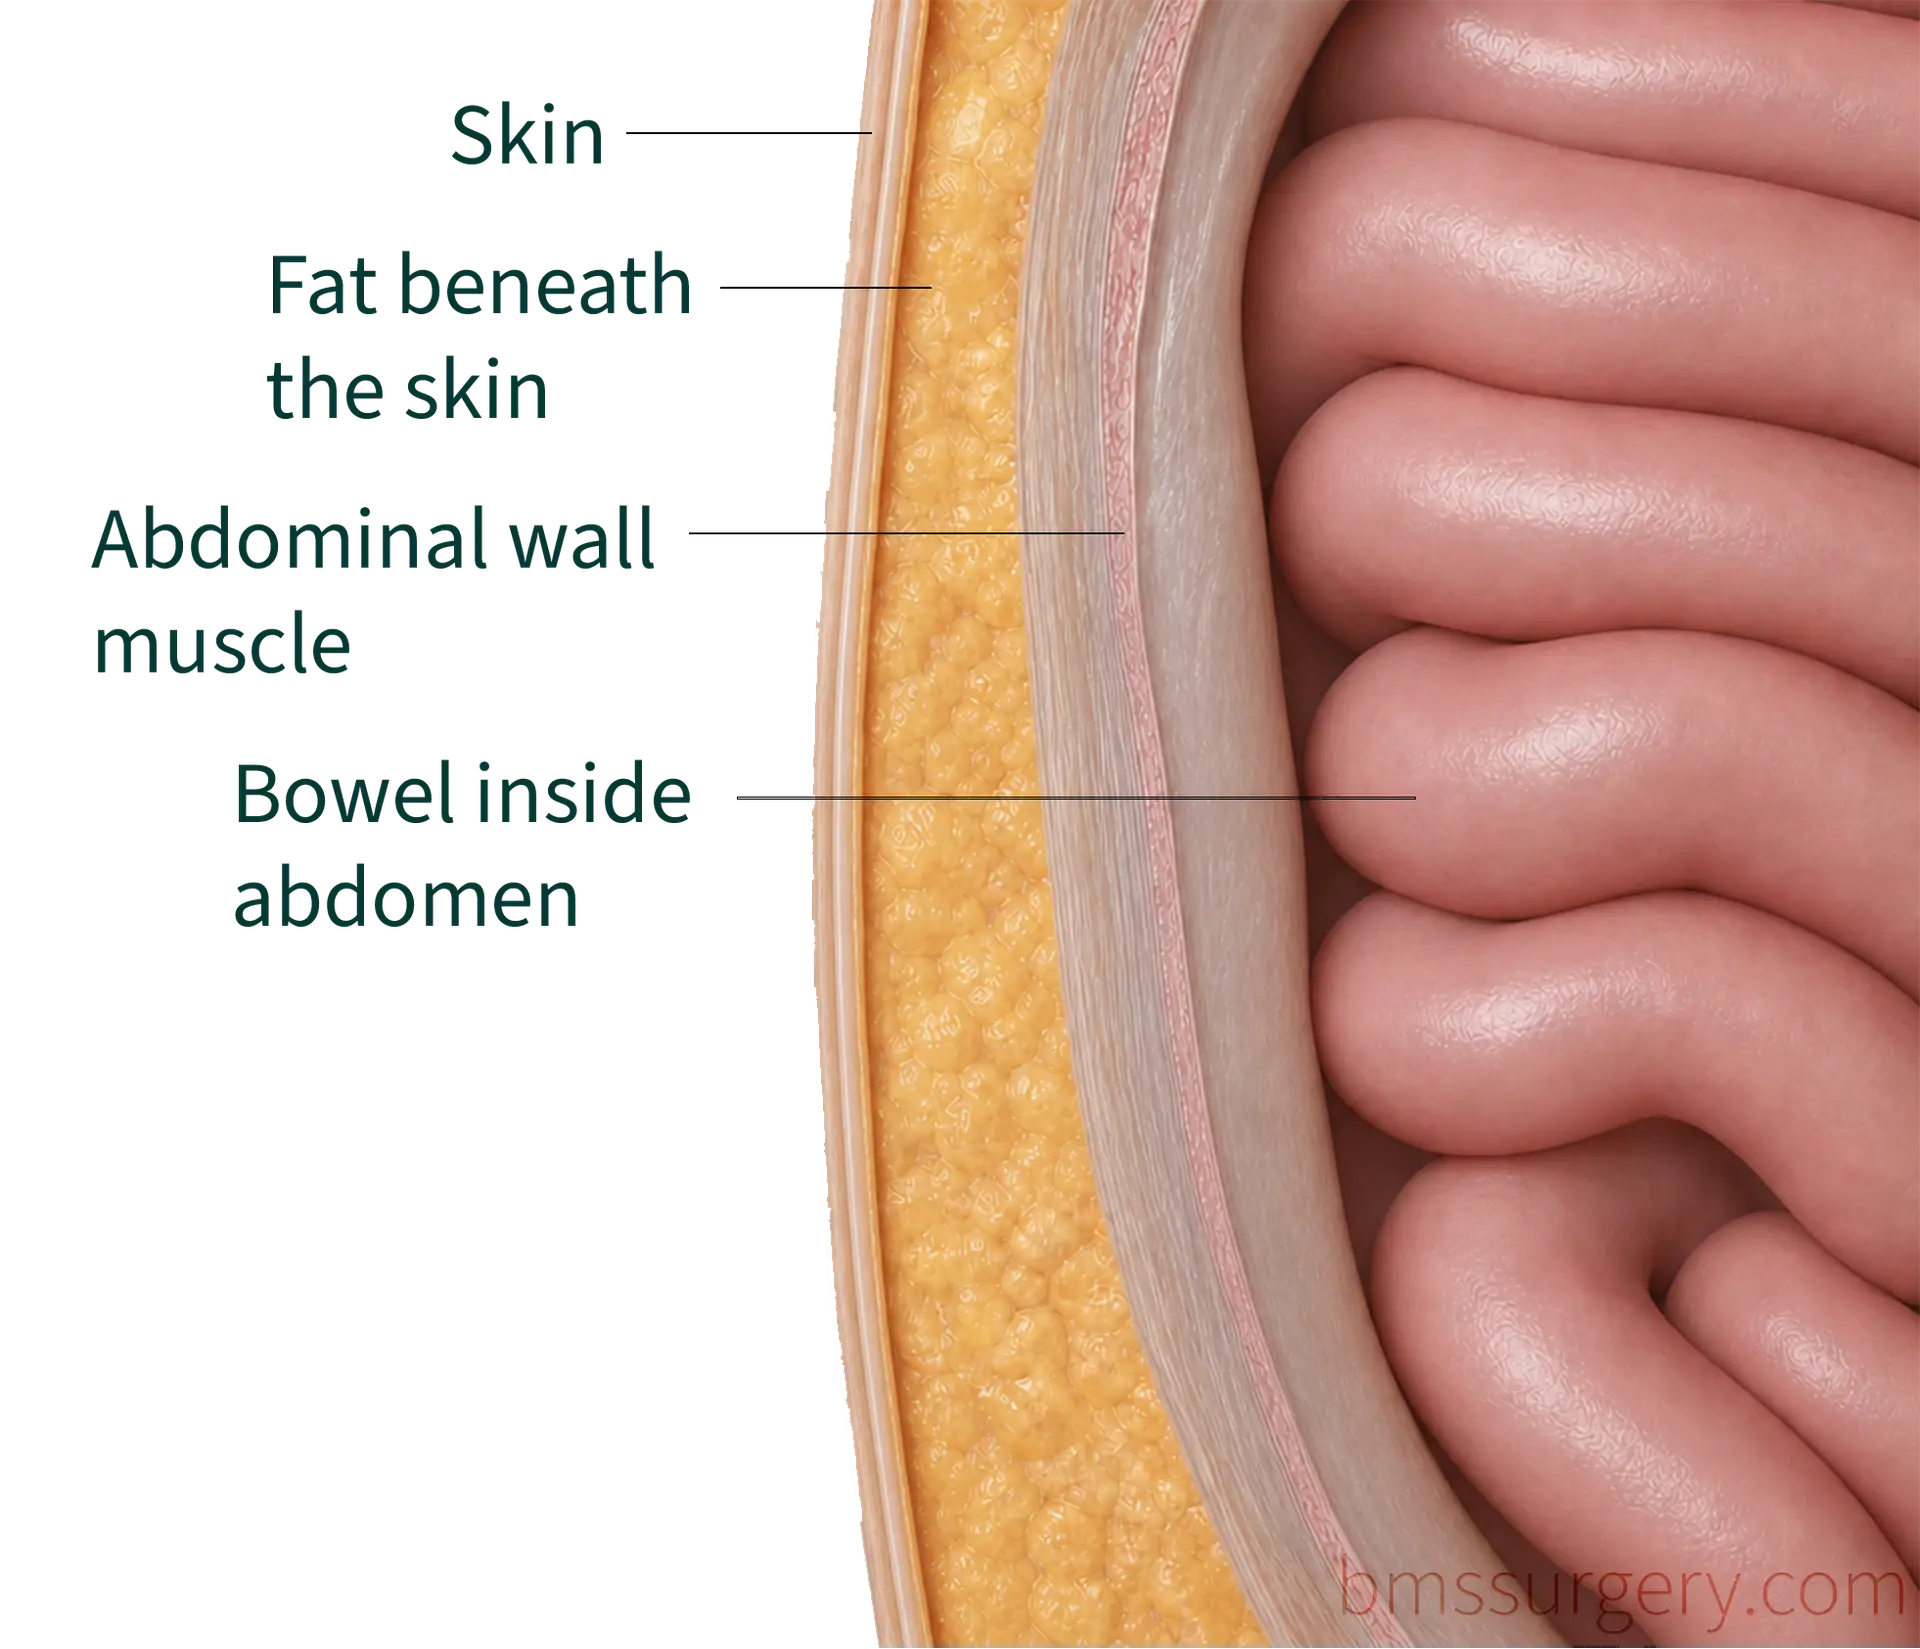
abdominal wall diagram

The abdominal wall

The abdominal wall is made of layers of muscle and strong connective tissue that hold everything inside in place. Some areas are naturally weaker, such as the groin, the belly button and any previous surgical scar. Heavy lifting, straining, a persistent cough, the way the muscles layers line up, or simply getting older can stretch these areas until a gap opens.

Typical symptoms: often none at first. In the early stages some people notice an ache or dragging feeling, especially at the end of the day.
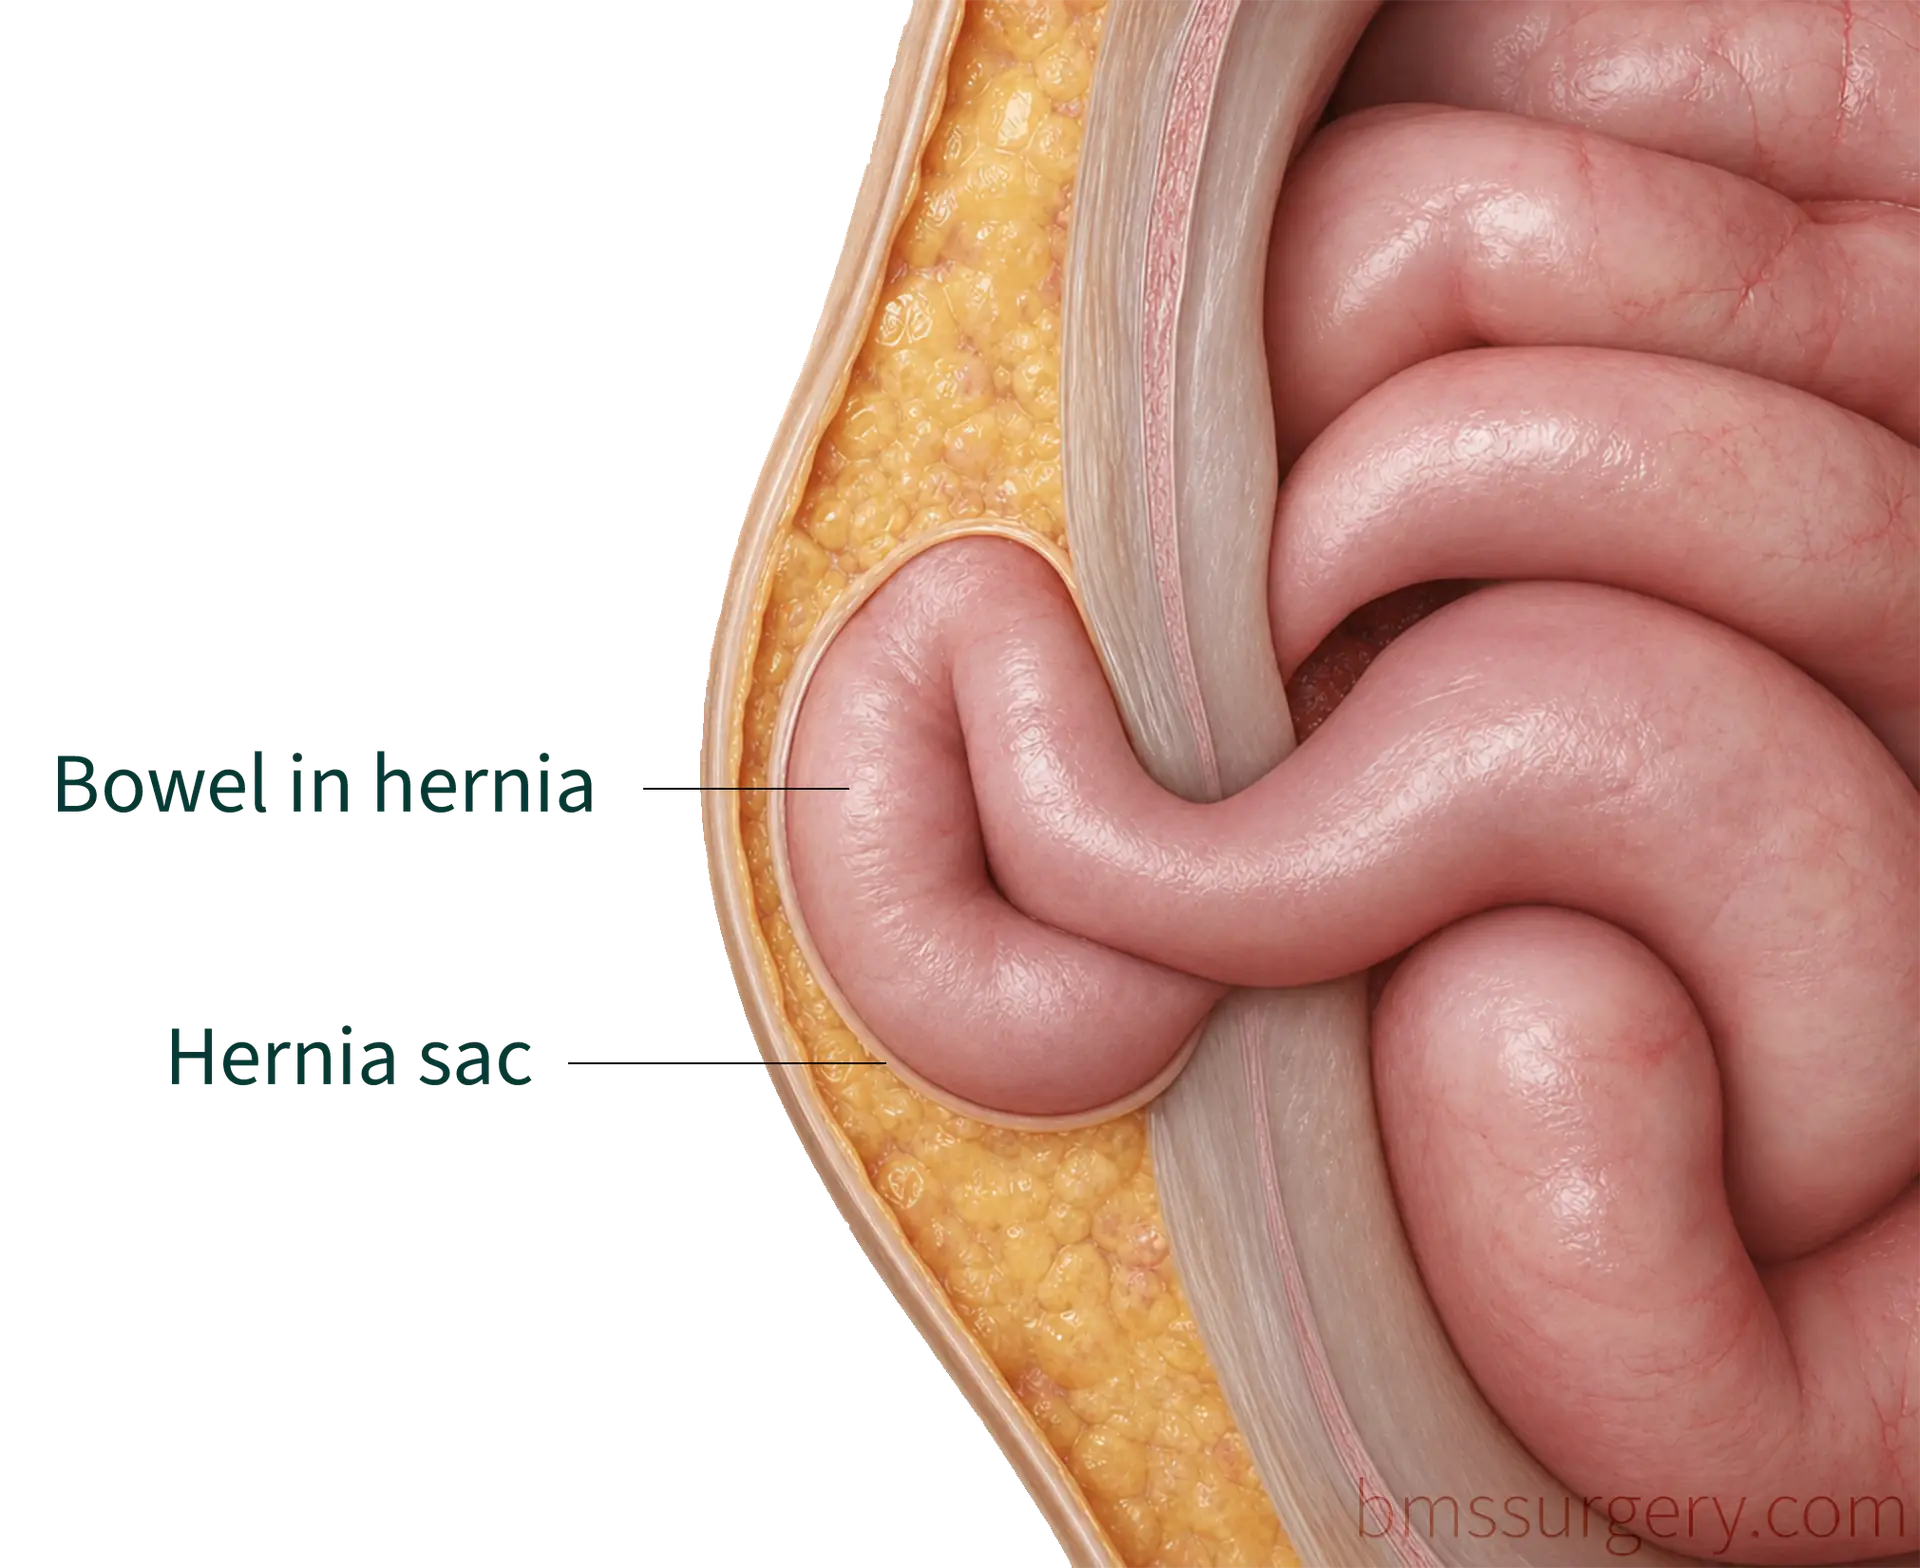
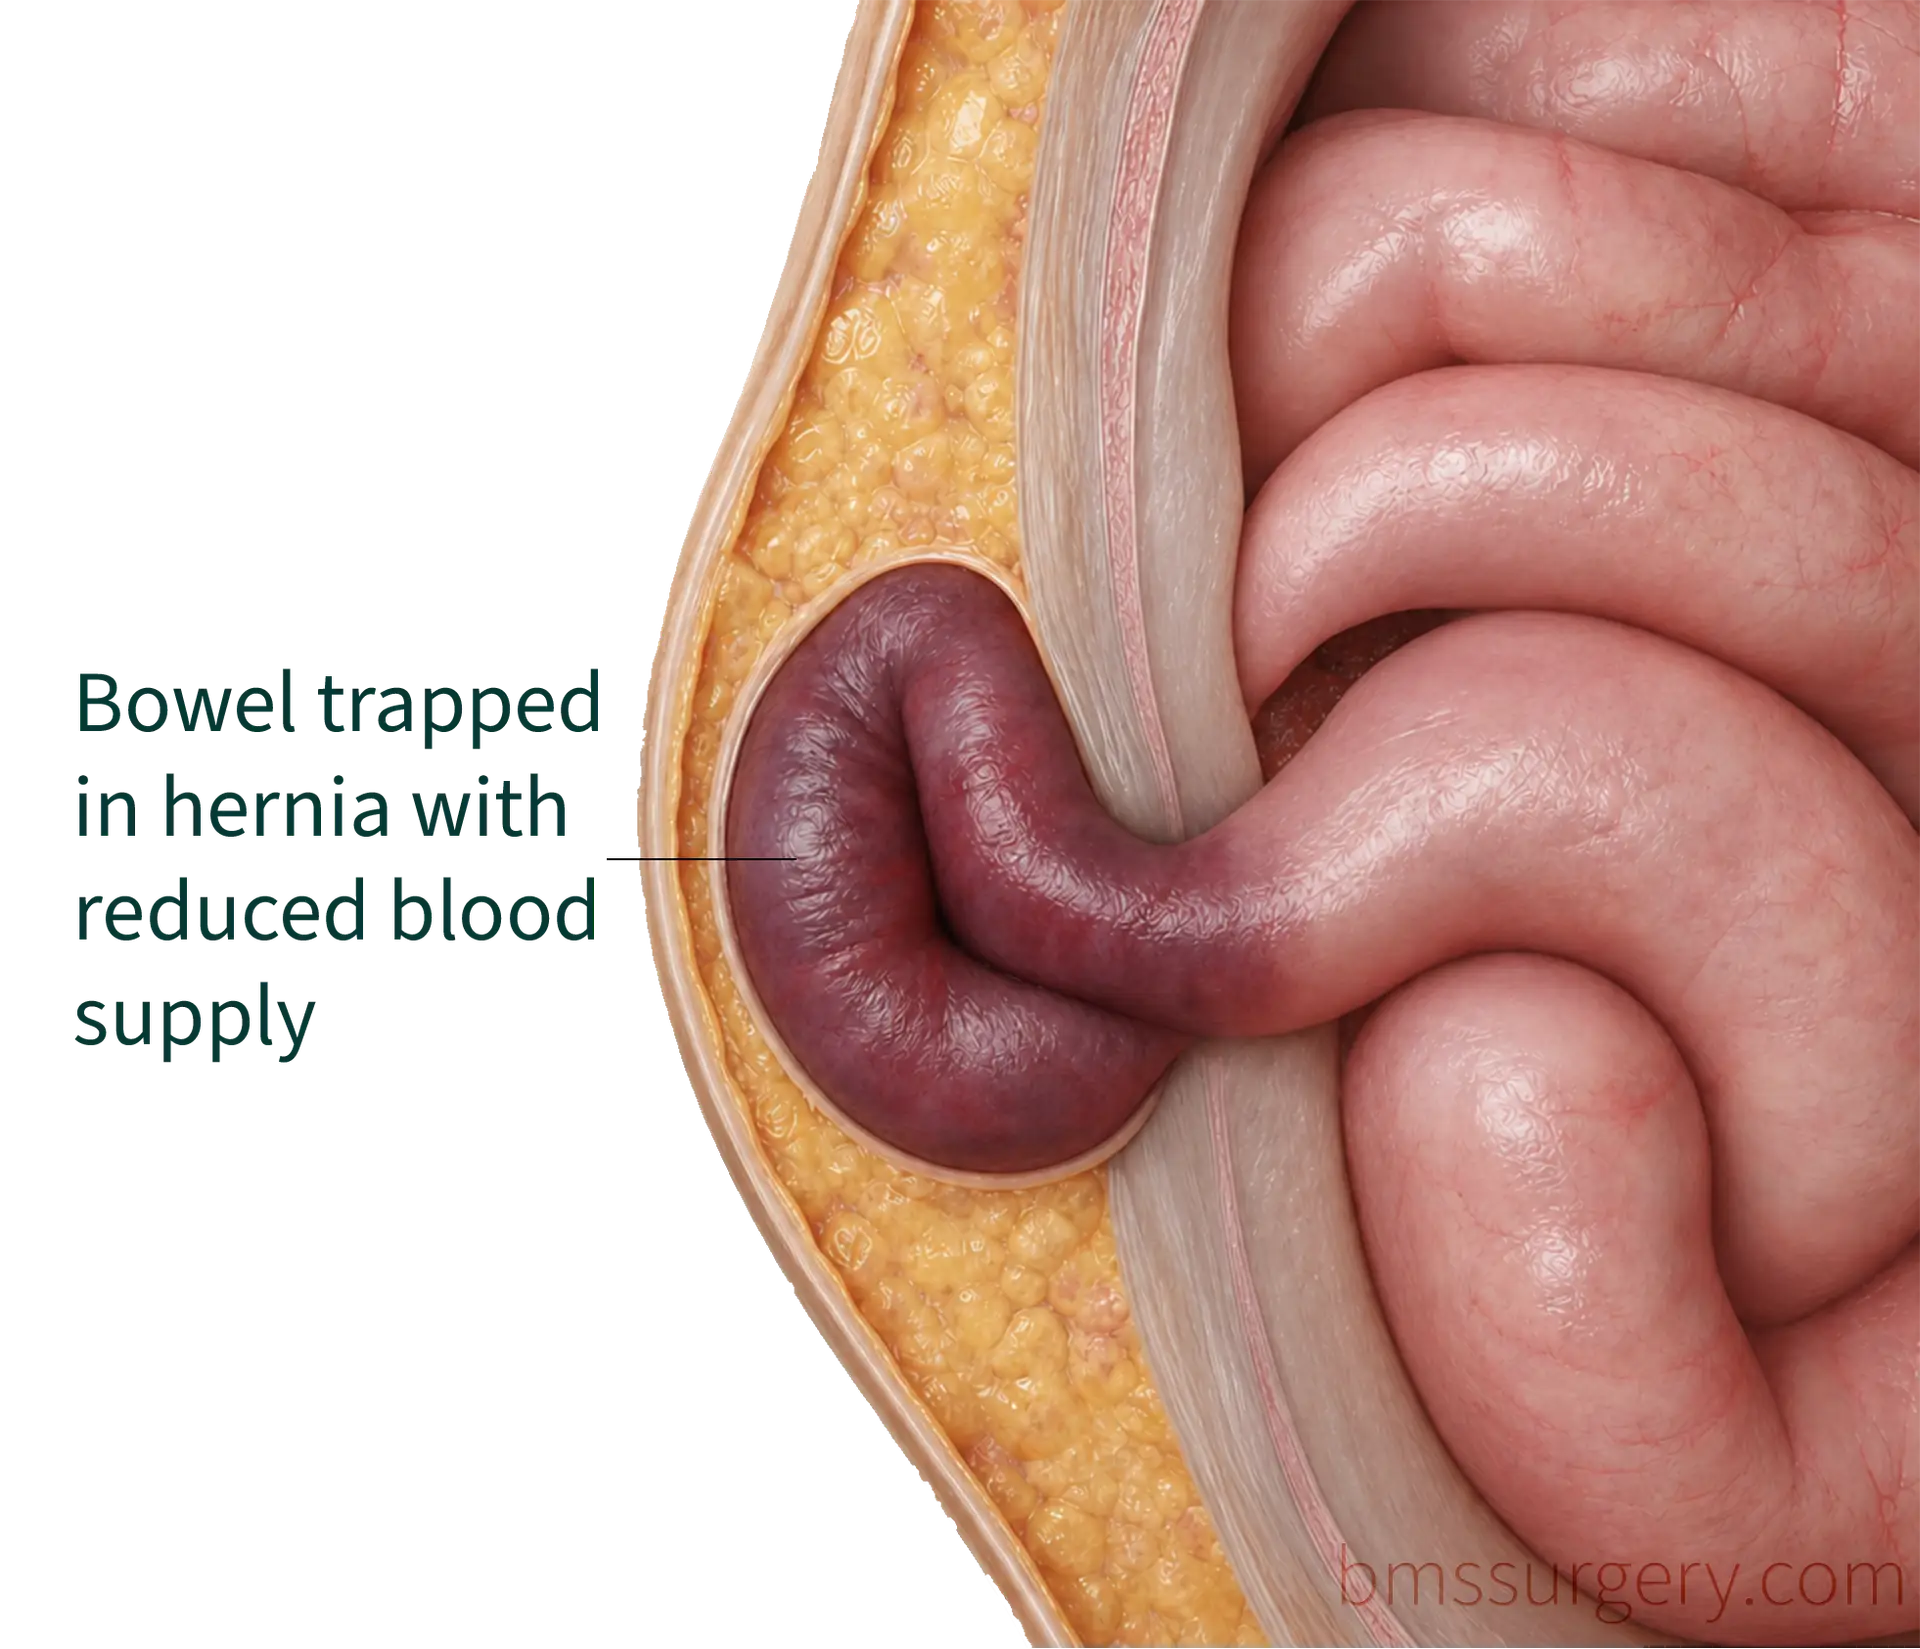
Types of hernia

Where can hernias occur?

Hernias are named after where they appear. Select a label on the diagram, or a name below, to find out more.
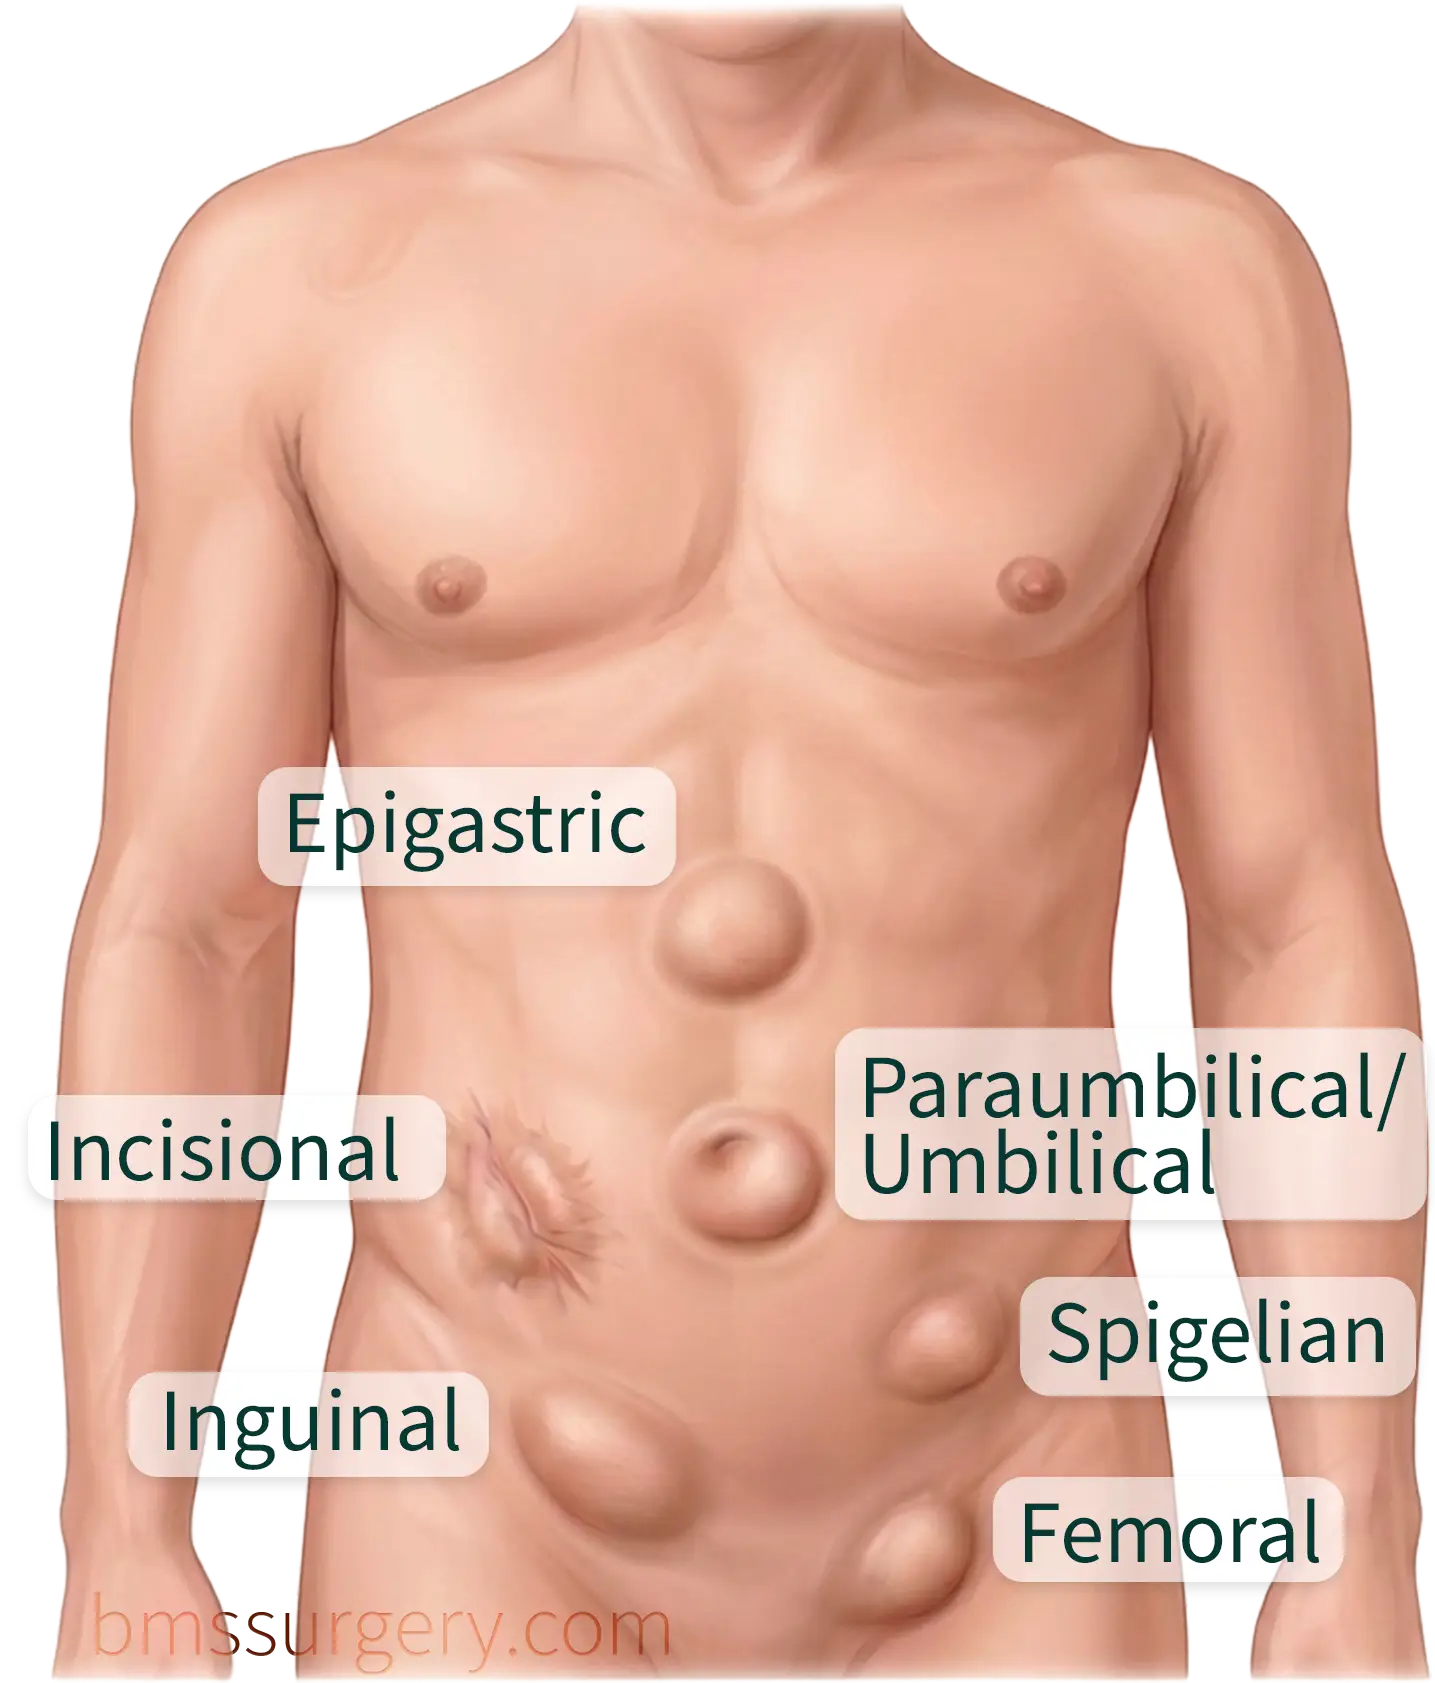
Diagram of a torso showing where epigastric, umbilical, incisional, Spigelian, inguinal and femoral hernias occur

Hernia lumps may vary in size and sometimes are not visible at all.

Where
Who
Repair

Understanding your diagnosis and treatment options

How a hernia is diagnosed, what hernia repair involves, and how to weigh surgery against leaving a hernia alone.

Most hernias are diagnosed by examination, and many people do not need a scan. A scan can help confirm the type and size of a hernia, find one that is difficult to feel, and plan the best repair. Ultrasound is commonly used for groin and abdominal wall hernias where the diagnosis may be uncertain. CT scans give detailed views of large, complex or hidden hernias. MRI may be used for groin or pelvic hernias that do not show on other scans, or to look for another cause of pain.

Examination and scans for hernias

1
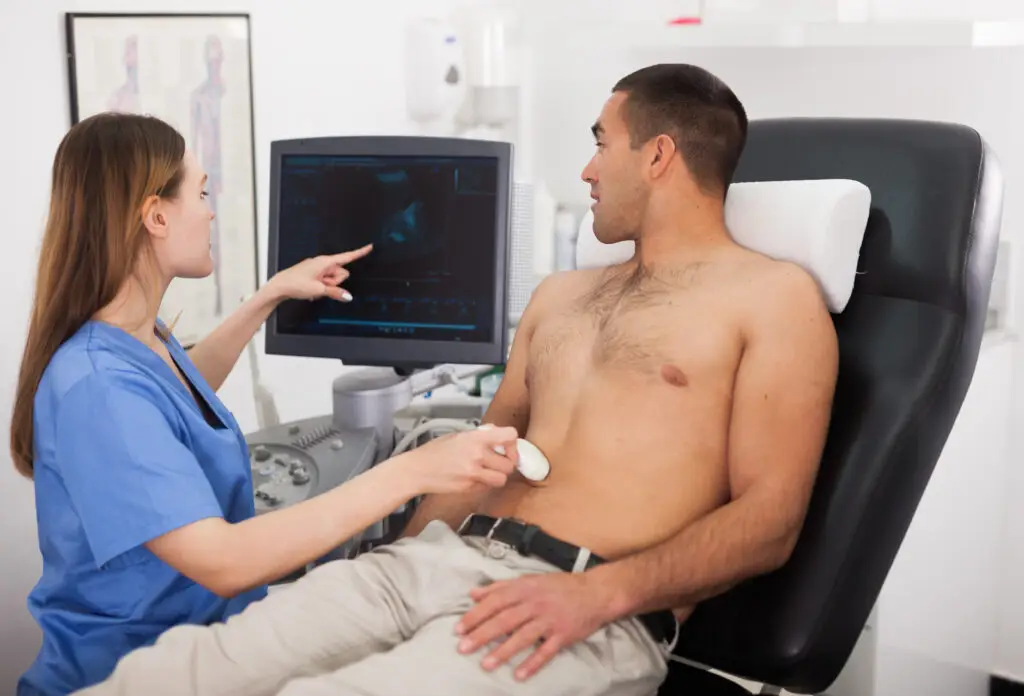
Ultrasound scan for gallstones

Ultrasound · groin and abdominal wall hernias
CT scan for gallstone related symptoms

CT · large, complex or hidden hernias
MRI scan for gallstones

MRI · groin pain with no clear cause

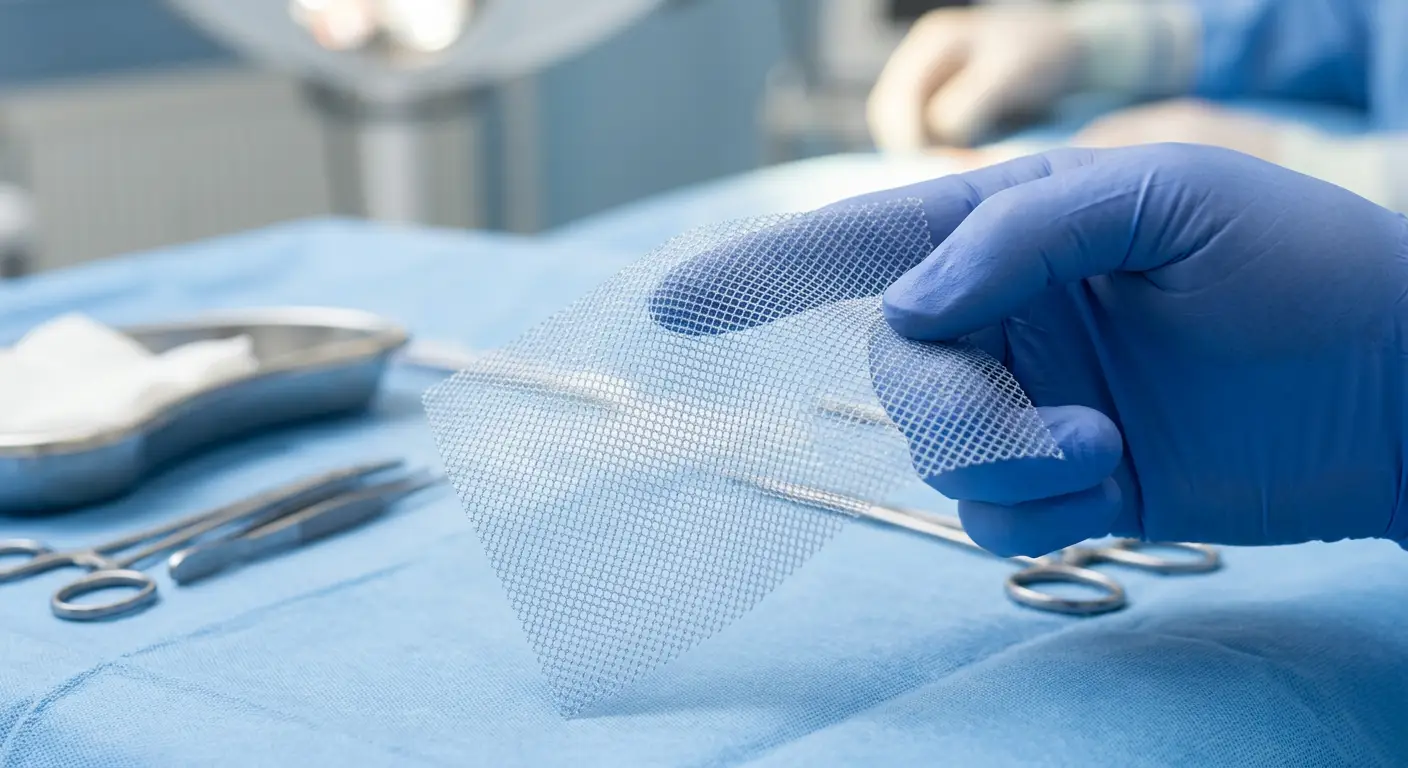
Hernia repair returns the tissue to its proper place and closes or reinforces the weak area in the abdominal wall. A hernia mesh is often used to strengthen the repair and reduce the chance of the hernia coming back. Hernia repair mesh is a thin, flexible medical material with a net-like appearance, similar to mosquito netting. Many hernias can be repaired by keyhole (laparoscopic) surgery, using small cuts and a camera, which can speed up recovery. Open surgery may be better for larger or complex hernias, or for hernias in certain locations. Large or recurrent hernias may need an abdominal wall reconstruction, a more extensive operation to restore the strength and shape of the abdominal wall.

Keyhole

or open, depending on your hernia

Mesh

often used to strengthen the repair

2 weeks

usual time off work

6–8 weeks

before heavy lifting

Hernia repair surgery

2
Keyhole surgery

Hernias are common and surgery is not recommended for everyone. Balancing the risks means weighing the chance of ongoing or worsening symptoms, and of complications from the hernia, against the risks of surgery. Hernias that cause no symptoms can generally be left alone, and if symptoms develop it is worth considering repair. Losing weight may improve symptoms, and for some people this means surgery can be avoided altogether. Femoral hernias are an exception: they are more likely to become trapped, so repair is usually recommended.

With surgery

Hernia repair is generally safe and usually relieves symptoms, but like all operations it carries risks. These include bleeding, infection, damage to nearby structures and the hernia coming back. Some people develop swelling from a fluid collection, and there is a risk of chronic (long-lasting) pain. There is also a chance of being worse after surgery than before.

Without surgery

A hernia does not heal on its own and may gradually get bigger and more uncomfortable. There is a risk of tissue becoming trapped or strangulated, which can be serious and needs emergency surgery. Some hernias cause a bowel blockage or limit daily activities.

Decisions are made on an individual basis after careful discussion

Balancing risks and benefits

3

Yes. If a hernia is not causing any symptoms, or the symptoms are mild, it may be best to avoid surgery altogether. A hernia will not heal on its own, but a hernia belt, truss or support can sometimes ease symptoms.

No. Most hernias are diagnosed by examination in clinic. If a scan would be helpful, it can be arranged after your consultation.

Hernia repair mesh is a thin, flexible medical material with a net-like appearance, similar to mosquito netting. It is used to reinforce the weakened area. Different types of mesh are available, each with its own benefits and potential drawbacks. Thousands of patients undergo hernia repair with mesh each year in Scotland alone and decades of research has gone into developing the products that are used today. Large studies have shown that mesh repair is a safe and effective way to treat hernias. The mesh reinforces the abdominal wall and reduces the risk of the hernia coming back. If a hernia does recur, further surgery may be more complex and can carry greater risks. Like all operations, hernia repair is not without potential complications. It is important to consider the risks and benefits specific to you carefully, and to make a decision based on your individual circumstances after assessment and discussion in clinic.

For groin hernias and smaller abdominal wall hernias we generally advise two weeks off work. Everyone is different and some people are back to work sooner. It is important to avoid heavy lifting for 6–8 weeks, as the strength of the repair develops as the body heals.

You should not drive until you can safely perform an emergency stop without pain or discomfort. It is also sensible to check your car insurance policy.

It is generally safe to fly around 10 days to 2 weeks after hernia surgery, provided recovery is going well and there have been no complications. You should be walking comfortably, eating and drinking normally. It is also sensible to check your travel insurance policy before travelling soon after surgery.

Frequently asked questions

4

You can read more about hernias and their treatment on this NHS website. This official guidance explains symptoms, when surgery may be needed, and what to expect from hernia surgery.

Mr Stutchfield is an approved provider to leading health insurers. If you are insured with another provider, please get in touch to confirm cover.